Tirzepatide may be better if you: Need a medication available right now : Tirzepatide is FDA-approved and available today through clinics and pharmacies Are sensitive to GI side effects : Lower overall side effect rates at every dose level Want established safety data : Years of post-marketing surveillance data available Have insurance coverage : Mounjaro/Zepbound may be partially covered Prefer a simpler titration : Uniform 2.5 mg steps are predictable and easy to follow Are a first-time incretin user : Extensive prescriber experience means better clinical support Retatrutide may be better if you: Have significant fatty liver disease : Liver fat reduction of up to 86% is unmatched Need maximum weight loss : 28.7% at 68 weeks exceeds all other compounds Have plateaued on tirzepatide : The glucagon component offers a new mechanism Are focused on metabolic health beyond weight : Triple agonism impacts more metabolic pathways Can tolerate higher GI burden : More side effects but more results Can wait for FDA approval : Expected late 2026-2027 for regulated access Neither compound is appropriate if you: Have a personal or family history of medullary thyroid carcinoma Have multiple endocrine neoplasia syndrome type 2 Are pregnant or planning pregnancy Have a history of severe psychiatric reactions to incretin therapies Have pancreatitis history (use with extreme caution) For researchers still undecided, the semaglutide vs tirzepatide comparison page provides additional context on how dual agonists compare to single agonists
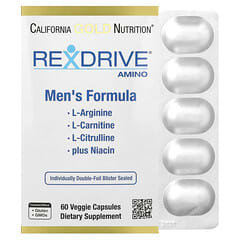
What can't be evaluated from publicly available information: whether the 30mg proprietary blend dose produces any measurable nitric oxide or vascular effect in humans, whether the brand's purity claims are substantiated by documented third-party testing, or what the split of the three amino acids is within the blend
Bupropion carries a well-documented interaction profile, inhibiting CYP2D6 and lowering the seizure threshold at higher doses [1]
It is important to emphasise that these potential benefits are largely theoretical or extrapolated from separate studies, rather than proven through robust clinical trials of the combination
[1] [9] [10] Hypothalamic-Pituitary Axis Disruption Patients with structural hypothalamic or pituitary abnormalities (e.g., tumors, post-surgical damage, or hypophysectomy) are not candidates for medications classified as growth hormone-releasing agonists