doi: 10.1016/S0149-2918(98)80104-5 176 KaleagasiogluFOlcayE
Onset patterns and course of myalgic encephalomyelitis/chronic fatigue syndrome
Journal of Blood Medicine
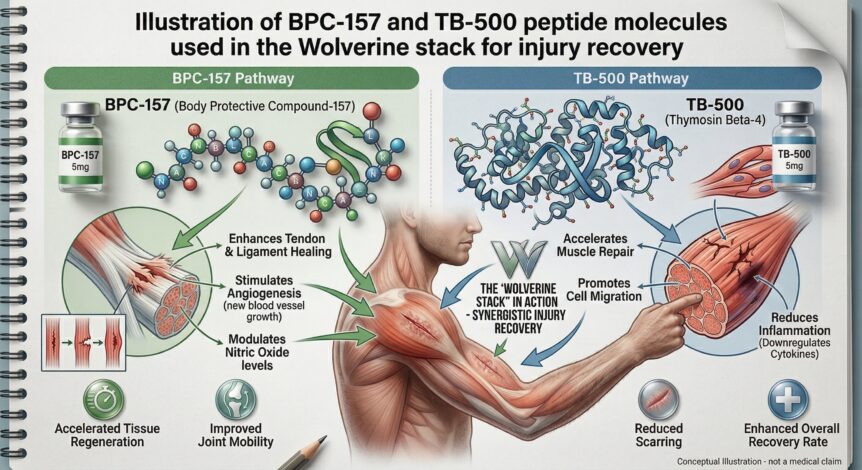
BPC-157 and the gutbrain axis: emerging links between cytoprotection and neuroregeneration More details Hide details 1 Department of Medical Biophysics, Faculty of Medical Sciences in Katowice, Medical University of Silesia, Katowice, Poland Corresponding author Barbara Pietrzyk Katedra i Zakad Biofizyki Lekarskiej, Wydzia Nauk Medycznych UM, ul

Theoretical concerns based on pharmacology include: Somatostatin-like effects -- binding sst1-5 could theoretically suppress GH release, insulin secretion, and glucagon release, though cortistatin's short half-life may limit systemic exposure Ghrelin receptor activation -- GHSR-1a activation could theoretically influence appetite and metabolism Unknown systemic effects -- the absence of any human administration data means that unexpected adverse effects cannot be excluded DSIP Side Effects# Limited human safety data from small studies: Headache -- occasionally reported Morning grogginess -- reported at higher doses, consistent with a sleep-promoting effect persisting beyond the intended sleep period Generally well-tolerated -- across the limited studies conducted, no serious adverse events have been attributed to DSIP No systematic safety characterization -- the absence of formal adverse event reporting, long-term follow-up, and immunogenicity testing means the safety profile is incompletely characterized Practical Applicability Comparison# Cortistatin# Cortistatin faces substantial practical barriers to sleep application: Route of administration -- all sleep studies used intracerebroventricular injection, which is only feasible in controlled research settings Short half-life -- rapid degradation in vivo limits duration of effect Somatostatin receptor cross-reactivity -- binding sst1-5 introduces potential metabolic and endocrine effects that complicate clinical development Research-grade only -- available only as a research peptide, not manufactured for clinical use Analog development -- structure-based analogs with improved selectivity and pharmacokinetics are being investigated but remain preclinical DSIP# DSIP is more practically accessible but still limited: Subcutaneous administration -- a clinically feasible route, unlike cortistatin's ICV requirement Available from research suppliers -- can be obtained, though quality varies between sources Very short half-life -- approximately 7-8 minutes, raising questions about whether meaningful sleep effects can be achieved given the rapid degradation No standardized protocol -- typical doses of 100-500 mcg pre-sleep are empirically derived, not established through dose-finding studies Stability concerns -- DSIP degrades in solution, adding practical challenges to preparation and storage Mechanism Specificity Comparison# This category highlights a fundamental scientific difference between the two peptides